Semaglutide’s appetite sites
A change in eating begins in particular circuits. Human trials then ask much larger questions.
Brainstem and hypothalamus
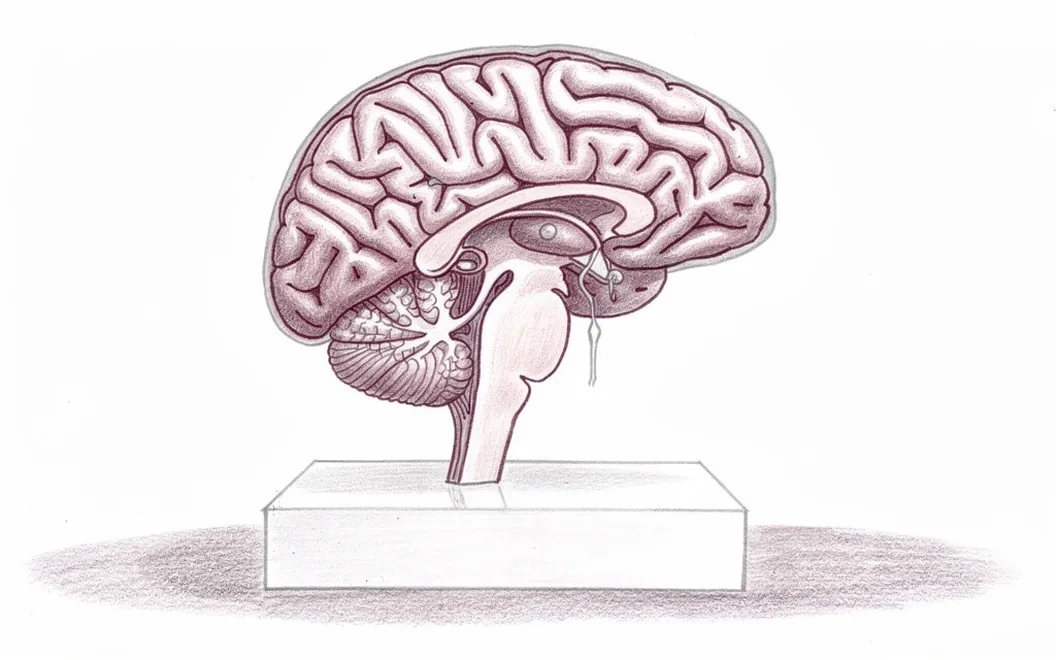
Semaglutide mimics GLP-1, a gut hormone involved in appetite and blood-sugar regulation. The rodent work on distributed neural pathways traced access to sites including the brainstem, hypothalamic arcuate nucleus and parabrachial nucleus. Food intake fell and food preference changed, with no decrease in energy expenditure.
I like the geographic precision: several sites contribute to an appetite effect that can sound singular in everyday conversation. The study was conducted in rodents. It helps explain a mechanism; the human weight result comes from a different kind of experiment.
Blood sugar and stomach emptying
GLP-1 receptor activity supports insulin release when blood sugar is elevated and suppresses inappropriate glucagon release. Slower stomach emptying is another action, relevant both to fullness and to gastrointestinal symptoms. The semaglutide safety review covers the clinical adverse-effect profile.
This breadth makes a single location an incomplete explanation. A single brain site seems too narrow an explanation for every weight change or episode of nausea. The pancreas, digestive tract and central circuits enter the account in different ways.
STEP 1 weight results
In STEP 1, 1,961 adults with overweight or obesity and no diabetes were studied for 68 weeks. Mean body-weight change was -14.9% with semaglutide and -2.4% with placebo. Those are whole-person measurements obtained in a defined clinical population.
The difference from the rodent paper is useful. One experiment traces appetite pathways; the other measures an outcome in people. I can put them alongside each other without pretending that the human trial assigns a share of the weight change to each brain site.
What the research shows
Head-to-head against a dual agonist. In a 72-week trial of 751 adults with obesity, semaglutide at its maximum tolerated dose produced -13.7% mean weight loss, compared with -20.2% for a dual GIP/GLP-1 agonist tested against it (P<0.001) — a roughly 6.5-percentage-point gap that places semaglutide as the benchmark newer, multi-receptor compounds are compared against, including this guide's own retatrutide [11].
Weight management (STEP 1). In 1,961 adults with overweight or obesity and no diabetes, once-weekly semaglutide produced -14.9% mean body weight at 68 weeks versus -2.4% with placebo — a treatment difference of roughly 12.4 percentage points [14].
Cardiovascular outcomes (SELECT). In 17,604 adults with established cardiovascular disease and overweight or obesity but no diabetes, semaglutide reduced the combined rate of cardiovascular death, non-fatal heart attack, or non-fatal stroke versus placebo (hazard ratio 0.80), a 20% relative risk reduction [13].
Kidney outcomes (FLOW). In 3,533 adults with type 2 diabetes and chronic kidney disease, semaglutide reduced a composite of kidney failure, major eGFR decline, or kidney/cardiovascular death versus placebo (hazard ratio 0.76), a 24% lower risk [12].
Cardiovascular outcomes in diabetes (SUSTAIN-6). In 3,297 adults with type 2 diabetes at high cardiovascular risk, semaglutide reduced the same three-part cardiovascular composite (hazard ratio 0.74), though rates of diabetic-retinopathy complications were higher in the semaglutide group (hazard ratio 1.76) [17].
Safety profile. A dedicated safety review characterizes semaglutide's overall risk-benefit balance as favorable in type 2 diabetes, with mostly mild-to-moderate gastrointestinal effects (nausea in roughly a third of patients), an increased risk of gallbladder disease, and pancreatic- and thyroid-cancer signals that remain unconfirmed given their low incidence [15].
These outcome numbers describe Semaglutide in defined trial populations, not a self-directed course of treatment; Promise Peptides (mypromise.com) currently prescribes semaglutide, with each prescription contingent on its licensed U.S. clinician's individual assessment. Its clinicians can turn a request down; its care is for patients in the United States, and a treatment listed in one state may be absent in another. FDA-approved semaglutide medicines exist, whereas a separately compounded semaglutide preparation has no FDA approval.

Eyes, gallbladder and gastrointestinal effects
The safety review describes gastrointestinal intolerance as the dominant adverse-effect burden and identifies increased biliary-disease risk. In SUSTAIN-6, the cardiovascular result accompanied higher rates of diabetic-retinopathy complications, with a hazard ratio of 1.76. The eye finding is discussed in the context of pre-existing retinopathy and rapid improvement in blood sugar.
The thyroid C-cell warning comes from rodent findings. A personal or family history of medullary thyroid carcinoma or MEN-2 is a contraindication; a clear human thyroid-cancer signal remains unconfirmed. Acute pancreatitis is also a class warning. These cautions require clinical assessment.
The speed-of-change explanation for retinopathy deserves my attention. It makes the starting condition of a tissue relevant to the outcome. That remains an explanation to examine, rather than permission to dismiss the complication.
Everyday accounts of appetite
People’s accounts often centre on food occupying less attention, smaller portions and reduced cravings. They also describe nausea, bowel changes, reflux and fatigue; some mention reduced interest in alcohol or hair shedding during rapid weight loss. These reports are anecdotal accounts, rather than clinical evidence, and cannot establish cause or how often an effect occurs.
The contrast between the quiet food thoughts and the noisy digestive complaints is hard to miss. I’d want both experiences represented in any discussion of how treatment feels. The clinical safety review provides a separate basis for discussing established adverse effects.
Approved medicines and compounded preparations
Semaglutide has FDA-approved medicines for type 2 diabetes, chronic weight management, cardiovascular risk reduction in the indicated population and, since 2025, MASH. A separately compounded preparation has no FDA approval and requires an individual prescribing decision.
The clinical studies describe particular medicines and populations. The comparison page sets their outcomes beside the mouse and cell research on MOTS-c and the investigational retatrutide trials.